




The Latest in ACL Rehabilitation
The Cross Bracing Protocol Explained:
The Latest in ACL Rehabilitation
Anterior cruciate ligament (ACL) injuries are among the most common and impactful injuries in sports medicine. Traditionally, ACL ruptures—especially complete ones—were considered irreparable and almost always managed surgically in active individuals. However, recent developments in bracing protocols have reopened the door to non-operative management, particularly for proximal ACL tears. The Cross Bracing Protocol (CBP) is one such innovation drawing attention in physiotherapy and orthopaedics.
This post explores the rationale behind the CBP, the evidence supporting it, how it works in practice, and key considerations for physiotherapists involved in early to mid-stage rehabilitation.
What is the Cross Bracing Protocol?
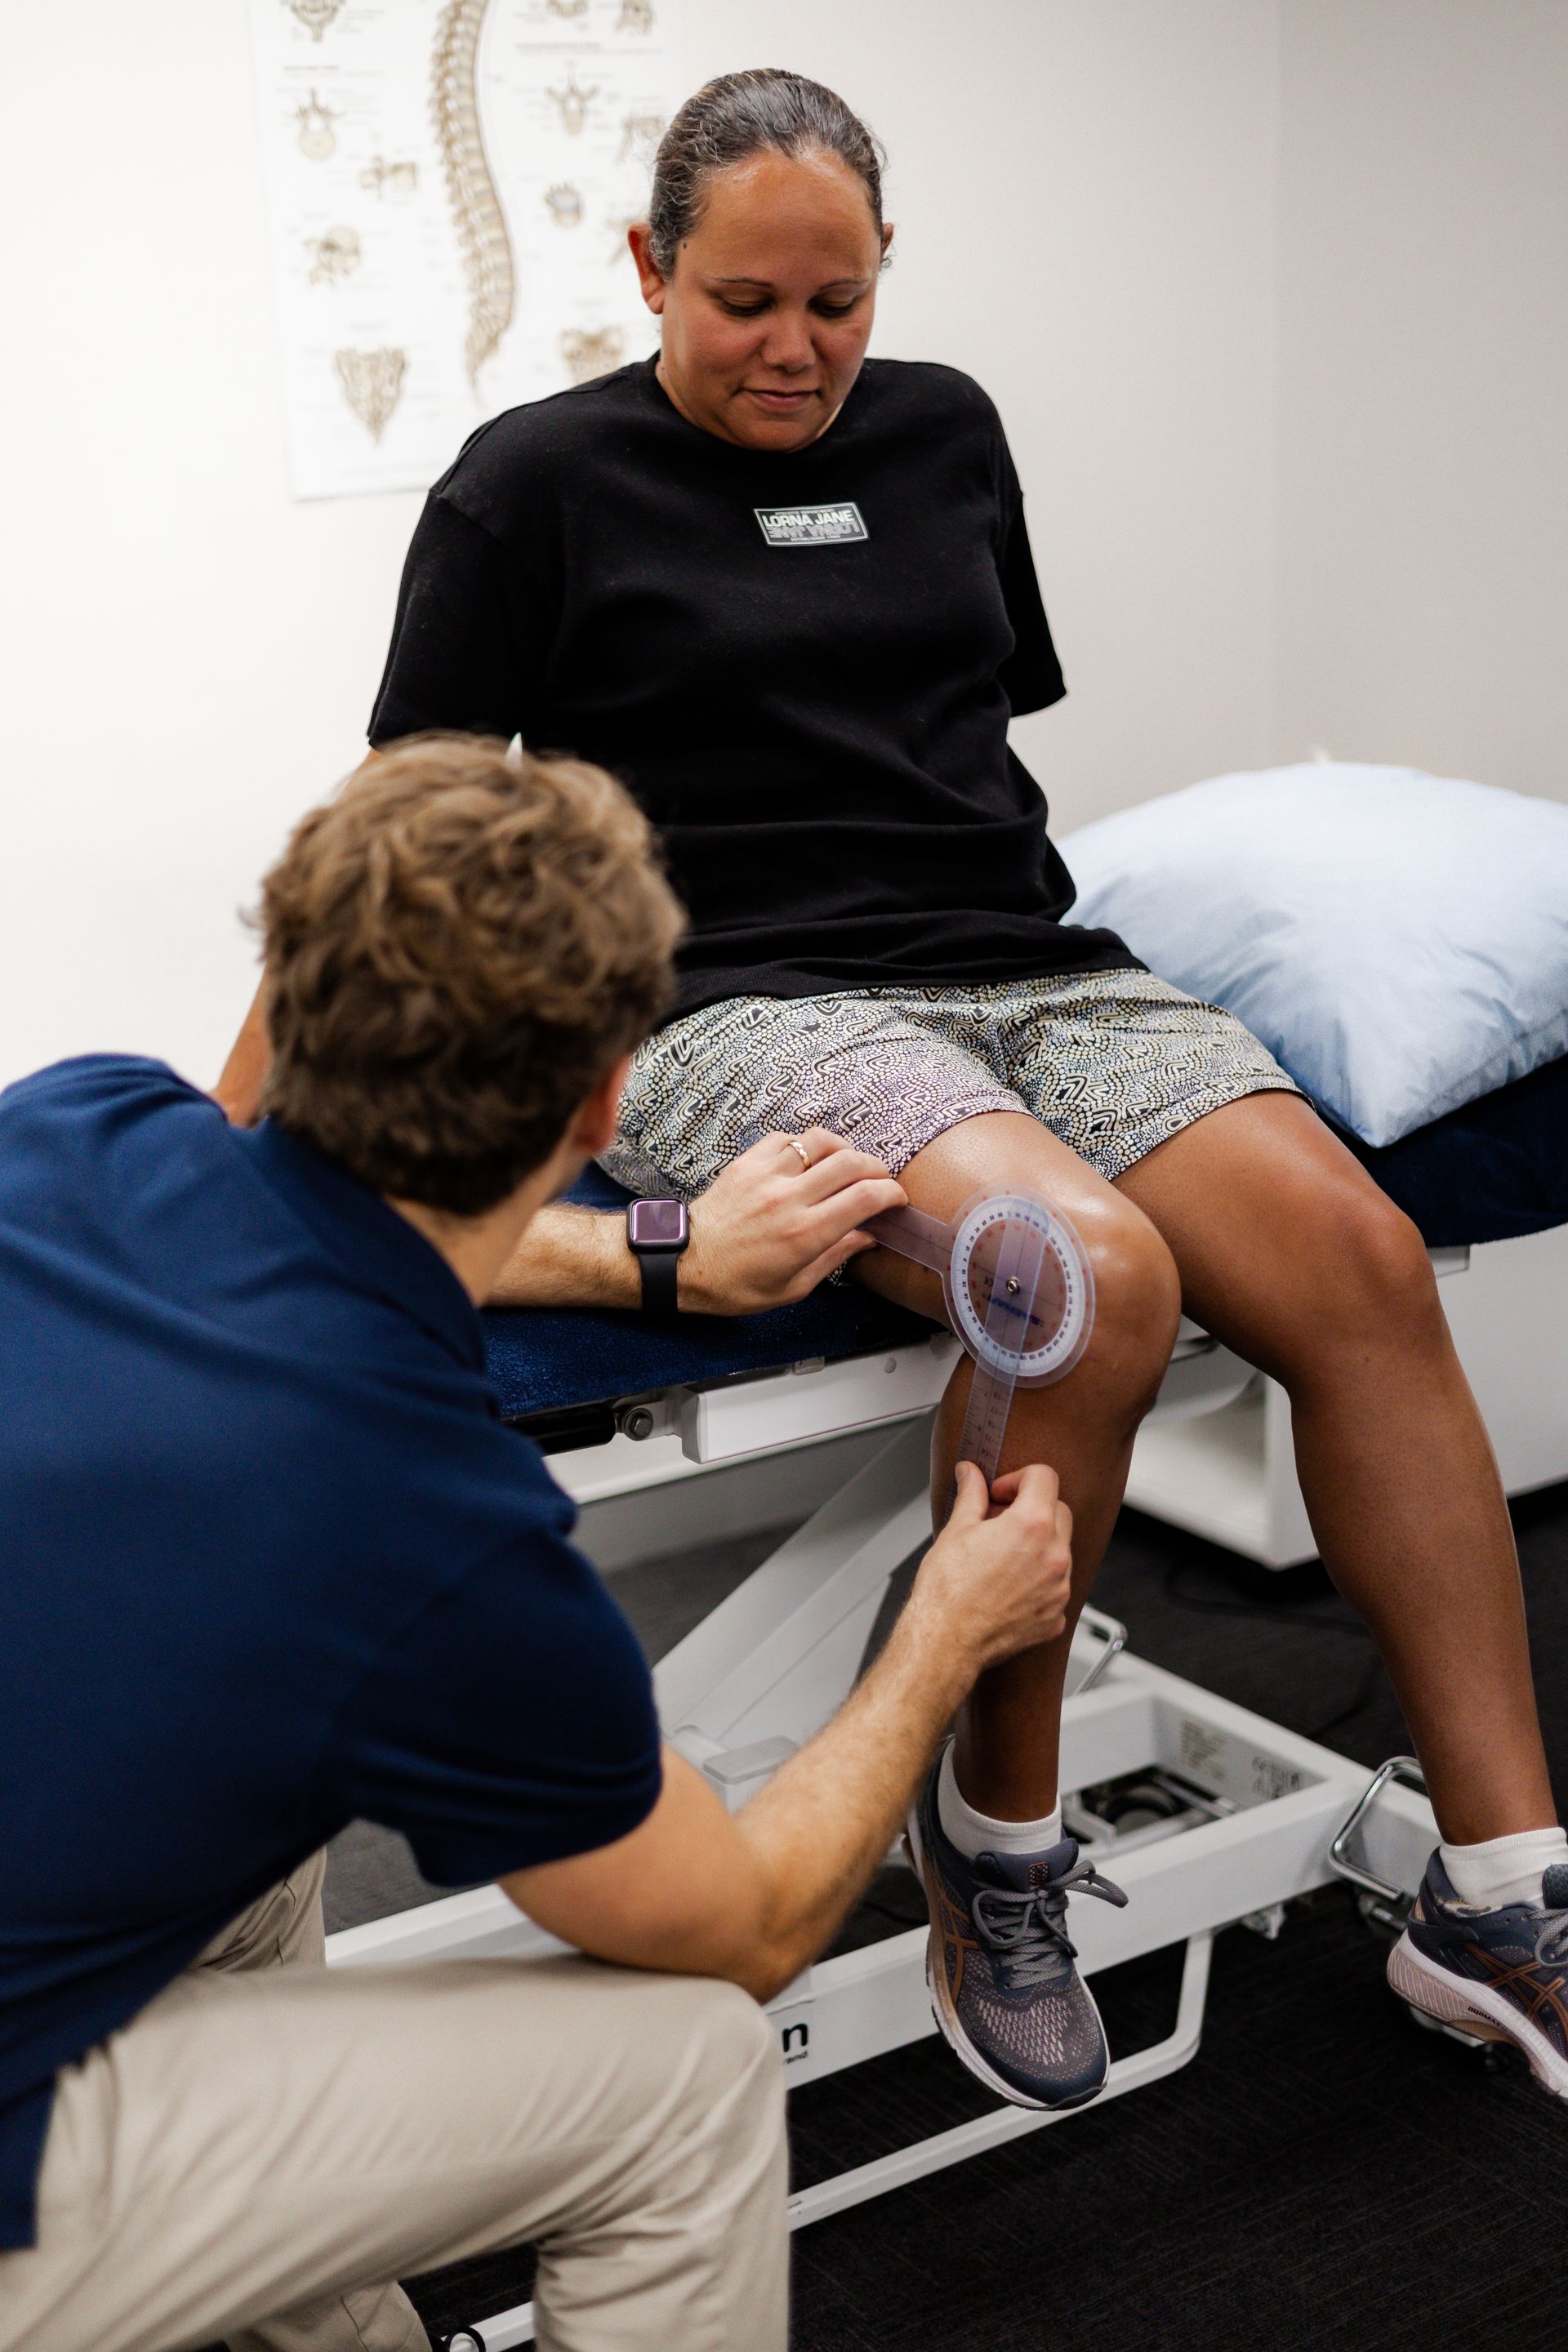
The Cross Bracing Protocol is a non-surgical approach developed primarily to treat proximal ACL tears—those close to the femoral attachment of the ligament. The protocol uses immobilisation in knee flexion (usually between 60–90 degrees) for a defined period, aiming to bring the torn ends of the ACL into close proximity to facilitate natural healing.
It challenges the long-held assumption that a ruptured ACL cannot heal and must be reconstructed. Instead, CBP posits that under the right mechanical conditions (reduced tension and improved ligament contact), biological healing is possible—similar to how MCL injuries often heal without surgery.
The Science Behind Ligament Healing
The idea that ACLs cannot heal stems from early studies that didn’t control for limb positioning or stability post-injury. However, we now understand that:
- Proximal ACL tears have better vascularity and cellular potential to heal.
- Immobilisation in flexion reduces tension across the ACL, preventing retraction of the torn stump.
- Mechanical stability (e.g., from bracing) is critical to allow bridging tissue to form.
A 2022 study by Murray et al. in The American Journal of Sports Medicine found that spontaneous healing of the ACL is possible in selected cases, particularly with bracing and early rehab supervision. From an exercise physiologist or sports physio.

Evidence Supporting the Cross Bracing Protocol
Several key studies and case series have explored the efficacy of CBP:
- Blachut et al. (2021, AJSM): In a case series of 80 patients with proximal ACL ruptures, over 70% showed MRI-confirmed healing at 12 weeks with CBP, and many returned to pre-injury levels of sport within 6–9 months.
- Burgi et al. (2023): Found that the healing ligament, although slightly different structurally from the native ACL, had sufficient continuity and functional stability for high-level sport participation.
- Systematic review (2024, Sports Med): Concluded that CBP is promising for selected patients and may reduce unnecessary surgeries in well-screened populations.
While the sample sizes remain modest and follow-up periods limited in some cases, the preliminary outcomes are compelling for those working with athlete physiotherapy services and sports rehabilitation centres such as Sports Lab Alexandria.
Who is Suitable for Cross Bracing?
Ideal candidates meet the following criteria:
- Acute, proximal ACL rupture, confirmed on MRI
- Minimal or no concomitant meniscal damage requiring repair
- No significant instability on initial manual testing when knee is braced
- Strong patient adherence and motivation
CBP is not suited to mid-substance or distal ACL tears, or to individuals with significant rotational instability. It also requires access to imaging and specialist review for ongoing monitoring – typically guided by an exercise physiologist or experienced physiotherapists in clinics like Marrickville Physio or Erko Physio.
Phases of the Cross Bracing Protocol
The protocol typically unfolds over 12–14 weeks and consists of the following phases:
Phase 1: Immobilisation in Flexion (Weeks 0–4)
- Position: Knee is braced at 90° flexion
- Goals: Promote ACL stump approximation and biological healing
- Intervention: Isometric quadriceps, hamstring co-contractions, hip strength maintenance, ankle pumps
Phase 2: Controlled Extension (Weeks 4–8)
- Gradual extension (10–15° per week) introduced via adjustable brace
- Continued quadriceps and hamstring activation
- Partial weight-bearing may begin by week 6
- MRI at week 6 often used to assess healing
Phase 3: Full Range and Load Reintroduction (Weeks 8–12)
- Brace removed around week 10–12 if healing is confirmed
- Focus on normalising gait, increasing strength, and proprioceptive training
- Begin cycling, bodyweight exercises, and balance drills
Phase 4: Return to Sport Prep (Weeks 12–24+)
- Progressive return to cutting, jumping, and sport-specific tasks
- Formal hop testing, Y-balance, and isokinetic testing to confirm readiness
Physiotherapist’s Role in CBP
The role of the physiotherapist is central throughout the CBP:
- Monitoring adherence: Bracing must be consistent. Poor compliance can disrupt healing.
- Progressive loading: The transition from isometric to dynamic exercise must be based on both clinical progress and imaging.
- Neuromuscular retraining: Emphasise hamstring and hip strength to reduce anterior tibial translation forces.
- Gait correction: Monitor for compensations during reintroduction of walking and jogging.
This is where collaboration between elite physiotherapists, remedial massage practitioners, and exercise physiologists becomes invaluable. Many patients also complement their program with remedial massage services, such as those located in Marrickville, Redfern Sydney, or Alexandria to assist with pain relief, flexibility, and circulation during rehab.
Limitations and Controversies
Despite its promise, CBP is not without criticism:
- Limited long-term data: Most studies report outcomes up to 12–24 months; re-tear rates long-term remain unknown.
- Lack of randomised trials: Most evidence is observational or from case series.
- Risk of stiffness: Especially if knee is immobilised in flexion too long without adequate rehab.
Some sports physicians argue that delaying surgery in non-responders may increase meniscal or chondral damage, especially in high-risk sports. This is why close collaboration with sports physiotherapists or massage and physiotherapy services is critical to ongoing management.
Conclusion
The Cross Bracing Protocol represents a shift in how we view ACL management. For select patients, particularly those with proximal tears—it offers a chance to heal without surgery, potentially reducing downtime, costs, and surgical risk. However, it demands careful patient selection, close monitoring, and a highly engaged rehab process
As the evidence base grows, physiotherapists, exercise physiologists, and sports physios are in a pivotal position to guide patients through this novel approach with a combination of structured rehabilitation, progressive loading, and functional testing.